


Higher Bebington, WirralGP-led · CQC registeredPatient FAQsJournalContact
The Skin & Joint Injection Clinic

Shoulder paintreatment inWirral.

Pain when you reach, dress, or lie on that side?

A man by a window in a navy coat, gripping the top of his painful shoulder as he dresses

Every painful shoulder has a reason.


GP-led · Ultrasound-guided
Person reaching up to a kitchen shelf while holding their sore shoulder
Living with shoulder pain

Start with what's actually hurting.

not the treatment name

Most shoulder pain doesn't arrive with a clean label. It just starts: dressing becomes awkward, sleep gets fragmented because you can't lie on that side, reaching for the seatbelt or a high shelf catches you out. Knowing whether you have frozen shoulder, rotator cuff tendinopathy, bursitis or arthritic change matters, because each responds to different care.

At the Skin & Joint Injection Clinic in Bebington, Wirral, we assess shoulder pain in person, including a careful history, examination and, where it helps, ultrasound to look at the tendons and bursa. The recommendation that follows is matched to what we find, not assumed in advance.

What might be causing it

The diagnoses we most often see in clinic.

These are the patterns of shoulder pain we most commonly assess. The list isn't diagnostic: your consultation works out which (if any) fits your symptoms.

Shoulder
pain

Tap a pattern
01

Hover or tap the points on the circle to explore each pattern.

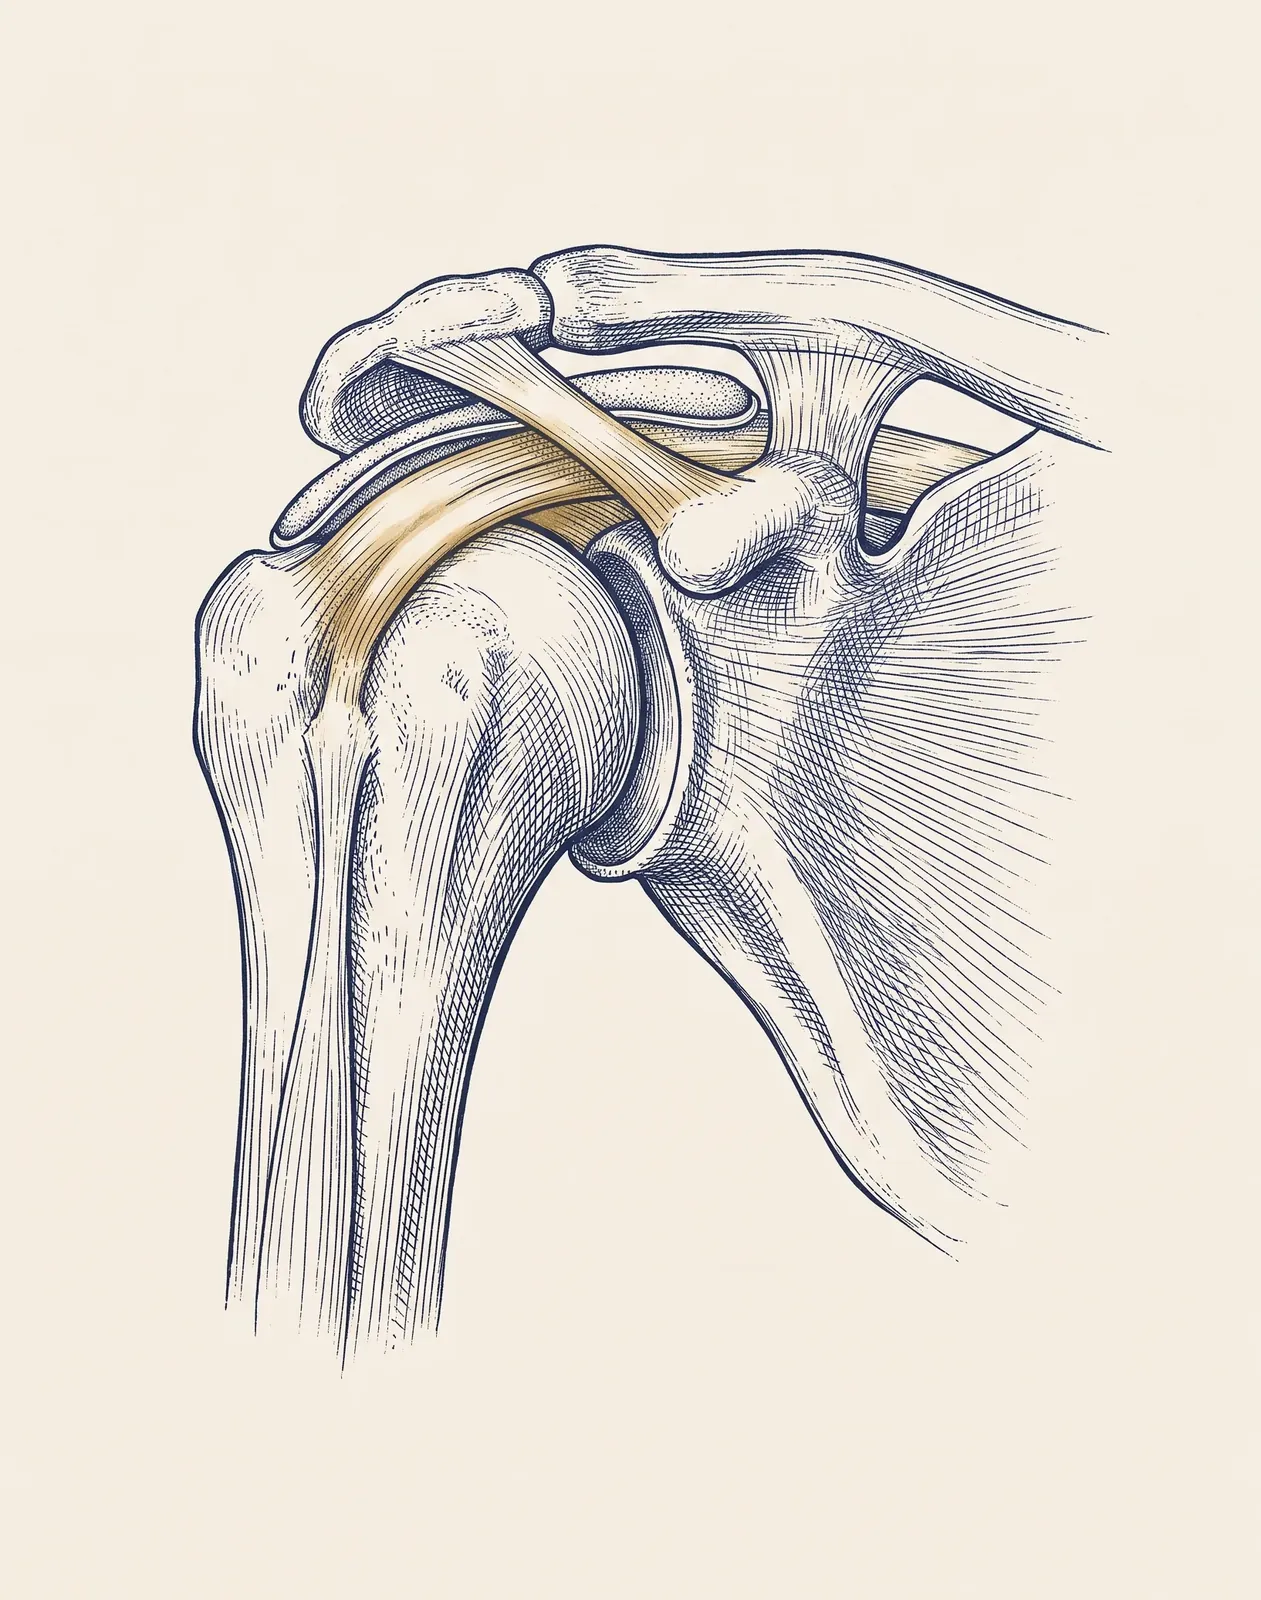
Engraved illustration of the shoulder showing the acromion, clavicle, AC joint, supraspinatus tendon, humeral head and glenoid
Why guidance matters

Precision matters in the shoulder.

  • Tendons
  • Bursa
  • Joint
  • AC joint

The shoulder packs the rotator cuff tendons, the subacromial bursa, the main joint and the small AC joint into a very small space. An injection only helps if it reaches the structure that's actually causing the pain.

That's why ultrasound is used during the procedure to guide the needle accurately, so the treatment is placed where it's needed rather than where it's hoped to land.

  • Ultrasound-guided injection
  • Tendons & bursa assessed on scan
  • GP-led, in Bebington, Wirral
Person reaching across their body for a seatbelt while holding the top of their shoulder
Pain on top of the shoulder?

The small joint that catches you out.

The acromioclavicular (AC) joint is where the collarbone meets the top of the shoulder blade: the bony bump you can feel on top of your shoulder. AC joint osteoarthritis causes localised pain at that bump, worse with cross-body movement and contact sports.

It's the joint you notice when you reach across for a seatbelt, fold your arms, put on a coat or lie on that side. Because the joint is small and sits just under the skin, accuracy matters, and ultrasound lets us see the joint line and place an injection precisely within it.

  1. 01Pain pinpointed on the bump at the top of the shoulder
  2. 02Worse reaching across the body: seatbelts, coats, folding your arms
  3. 03Often aches when lying on that side or lifting overhead
Which injection might suit your shoulder?

A starting point, not a diagnosis.

Patterns of pain matter as much as imaging. Below are the routes we most often discuss for shoulder problems. Final recommendation always follows in-person assessment.

01
If your pattern is

Frozen shoulder in the painful 'freezing' phase, with severe night pain limiting sleep and rehabilitation.

Often considered

Steroid injection

Targeted into the glenohumeral joint, used to settle severe pain enough to allow physiotherapy to progress. Often a turning point in the early phase of the condition.

Read more about steroid injection →


03
If your pattern is

Glenohumeral osteoarthritis where a non-steroid route is preferred, particularly if steroid injections have lost effect.

Often considered

Ostenil Plus (hyaluronic acid)

Considered for arthritic shoulder pain where the joint surface is the driver. Suitable for patients with diabetes and those wishing to avoid repeated corticosteroids.

Read more about Ostenil Plus →
04
If your pattern is

Chronic rotator cuff tendinopathy that hasn't progressed with rehabilitation and steroid injection.

Often considered

Platelet-Rich Fibrin (PRF)

An autologous regenerative option for chronic tendon problems where conventional approaches have plateaued. Considered after careful structural assessment on ultrasound.

Read more about PRF →
05
If your pattern is

AC joint osteoarthritis: pain on the bump at the top of the shoulder, worse reaching across the body or lifting overhead.

Often considered

Ultrasound-guided AC joint injectionNew

A small-volume steroid injection placed precisely into the acromioclavicular joint under ultrasound guidance. Settling the joint can ease pain enough to get back to strengthening and overhead activity, and a good response also helps confirm the AC joint as the source of the pain. Where arthritis in the joint is the driver and steroid is best avoided, a hyaluronic acid option may be discussed.

Read more about steroid injection →

Treatments are considered after clinical assessment. We do not offer or recommend injection therapy without first confirming the diagnosis and screening for contraindications.

Pain · Rehabilitation · Function

Three steps back to an easier shoulder.

For a shoulder, an injection is usually the step that makes physiotherapy possible, not a replacement for it.

First

Find the cause

An in-person consultation: history, examination and, where it helps, ultrasound of the tendons, bursa and joints.

Then

Settle the pain

Where it's the right option, a targeted ultrasound-guided injection calms night pain and inflammation enough for rehabilitation to start, or to progress where it had stalled.

Person doing a shoulder exercise with a resistance band at home

Finally

Rebuild strength

Structured physiotherapy restores range and rebuilds the rotator cuff and shoulder-blade muscles, so reaching, dressing, sleeping on that side and lifting overhead come back, with onward referral when surgery is the right conversation.

Frozen shoulder

A long road, often shortened.

Frozen shoulder typically runs its course over 12 to 24 months without treatment, moving through painful, frozen and thawing phases. A well-timed steroid injection during the painful phase, combined with structured physiotherapy, often shortens this timeline and reduces the night pain that disrupts everyday life.

Phases overlap and vary from person to person.

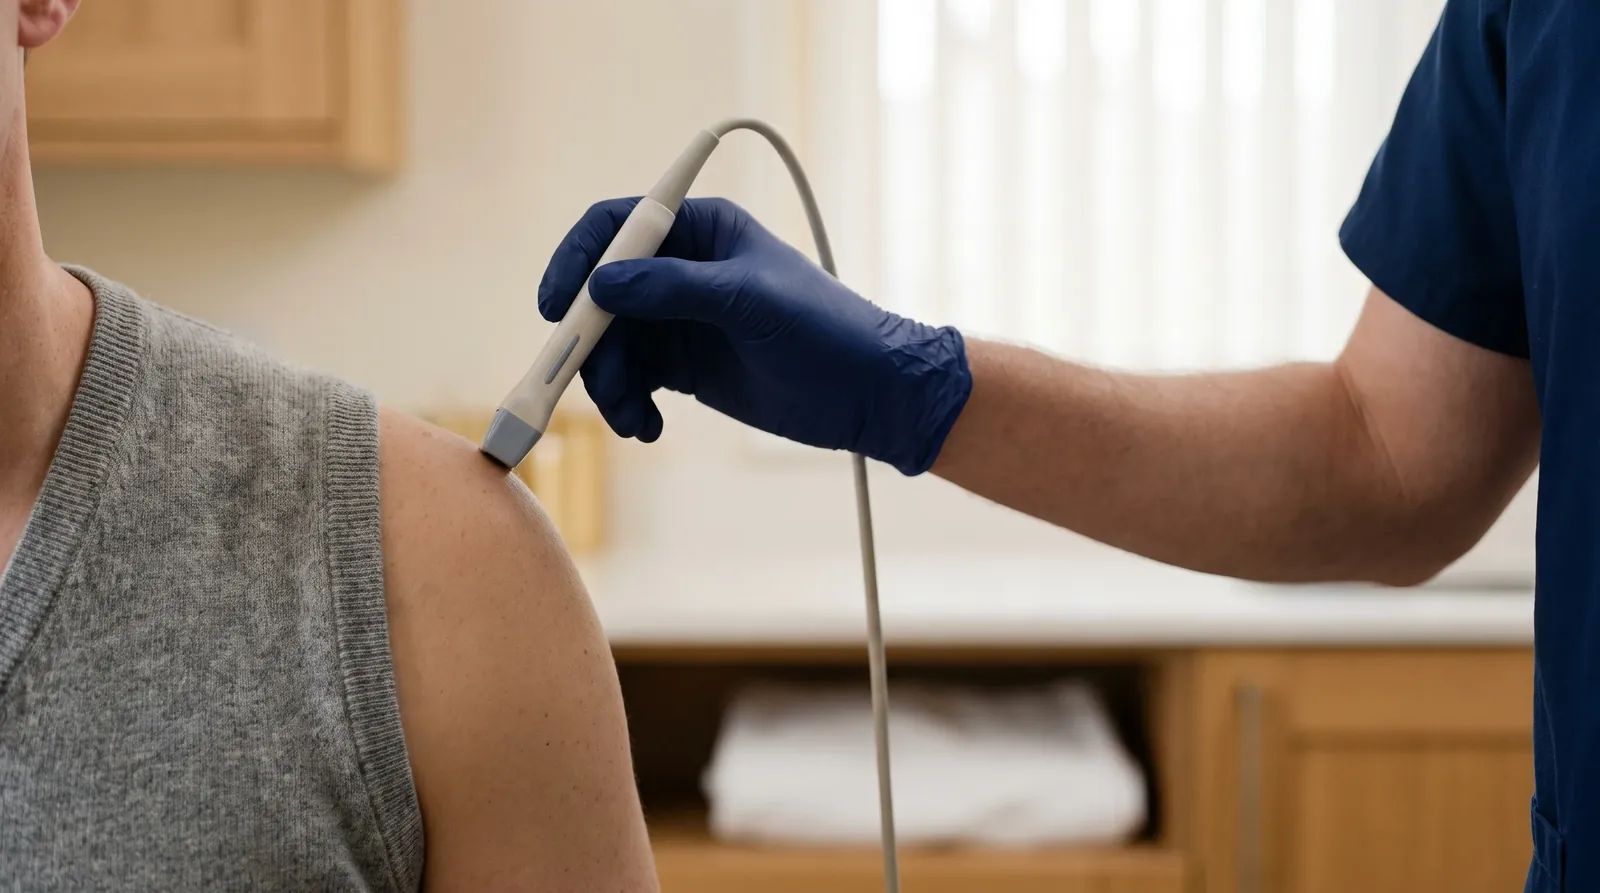
Clinician placing an ultrasound probe on a patient's shoulder
Do I need a scan first?

Often not. The scan happens at the injection.

Clinical examination and a clear history are usually enough to plan the right injection. Ultrasound is then used during the procedure to guide the needle. MRI is occasionally helpful when the diagnosis is unclear, surgery is being considered, or a significant rotator cuff tear is suspected.

The Skin & Joint Injection Clinic

Book an assessment for your shoulder in Wirral.

Our GP-led clinic in Higher Bebington serves patients from across Merseyside: Liverpool, Birkenhead, Heswall and Chester. We assess in person before any treatment is offered, and refer onward when it's the right call.

Frequently asked

Questions we hear about shoulder pain.

The questions patients most often raise in clinic when they're not sure which next step is right.

My shoulder is painful at night: what's likely going on?

Night pain in the shoulder commonly reflects subacromial bursitis, rotator cuff tendinopathy, frozen shoulder or AC joint osteoarthritis. Each behaves differently and responds to different treatment. The pattern of what brings the pain on, what eases it, and how it has changed over time is more useful than any single test for working out which is in play.

How long does frozen shoulder usually last?

Frozen shoulder typically runs its course over 12 to 24 months without treatment, moving through painful, frozen and thawing phases. A well-timed steroid injection during the painful phase, combined with structured physiotherapy, often shortens this timeline and reduces the night pain that disrupts everyday life.

Do I need a scan before a shoulder injection?

Often not. Clinical examination and a clear history of how the symptoms started and behave are usually enough to plan the right injection. An ultrasound is often used during the procedure itself to guide the needle accurately. MRI is occasionally helpful when the diagnosis is unclear, when surgery is being considered, or when a significant rotator cuff tear is suspected.

Will an injection fix a torn rotator cuff?

An injection won't repair a torn tendon. Where rotator cuff tears are partial and the patient isn't a surgical candidate, a steroid injection can reduce associated bursitis and pain enough to support rehabilitation. Larger or full-thickness tears in patients who want full function back are usually a surgical conversation, and we refer onward when that's the right path.

Can the AC joint be injected?

Yes, where the assessment points to the AC joint as the source of pain. It's a small, shallow joint, so the injection is placed under ultrasound guidance to make sure it goes into the joint itself. As with any injection, it works best alongside exercises that strengthen and support the shoulder, and we discuss the realistic benefit and alternatives first.

Shoulder pain?
Book →