 Outer elbow
The pan that feels heavier.
Lifting a cast-iron pan off the hob, palm down, and a sharp pain flares on the outer side of the elbow. It's often worse with gripping, lifting and rotating the wrist.
Often seen with Tennis elbow →Assessment for tennis elbow, golfer's elbow, bursitis and arthritic elbow pain.
No obligation · GP-led assessment first. Not ready to book? Meet Dr Mugerwa →

Pain when you grip, lift or turn?
Tennis elbow and golfer's elbow are some of the most stubborn musculoskeletal problems we see. They start as a niggle, get ignored because the elbow is awkward to rest, and gradually settle into a chronic pattern that affects work, sleep and the activities you enjoy. The good news is that the diagnosis is usually clear, and the right sequence of care tends to work.
At the Skin & Joint Injection Clinic in Bebington, Wirral, we assess elbow pain in person: examination, ultrasound where it helps, and an honest conversation about whether an injection is the right next step or whether rehabilitation needs more time. For chronic tendinopathy that has plateaued, regenerative options such as PRF often make more sense than another steroid injection.
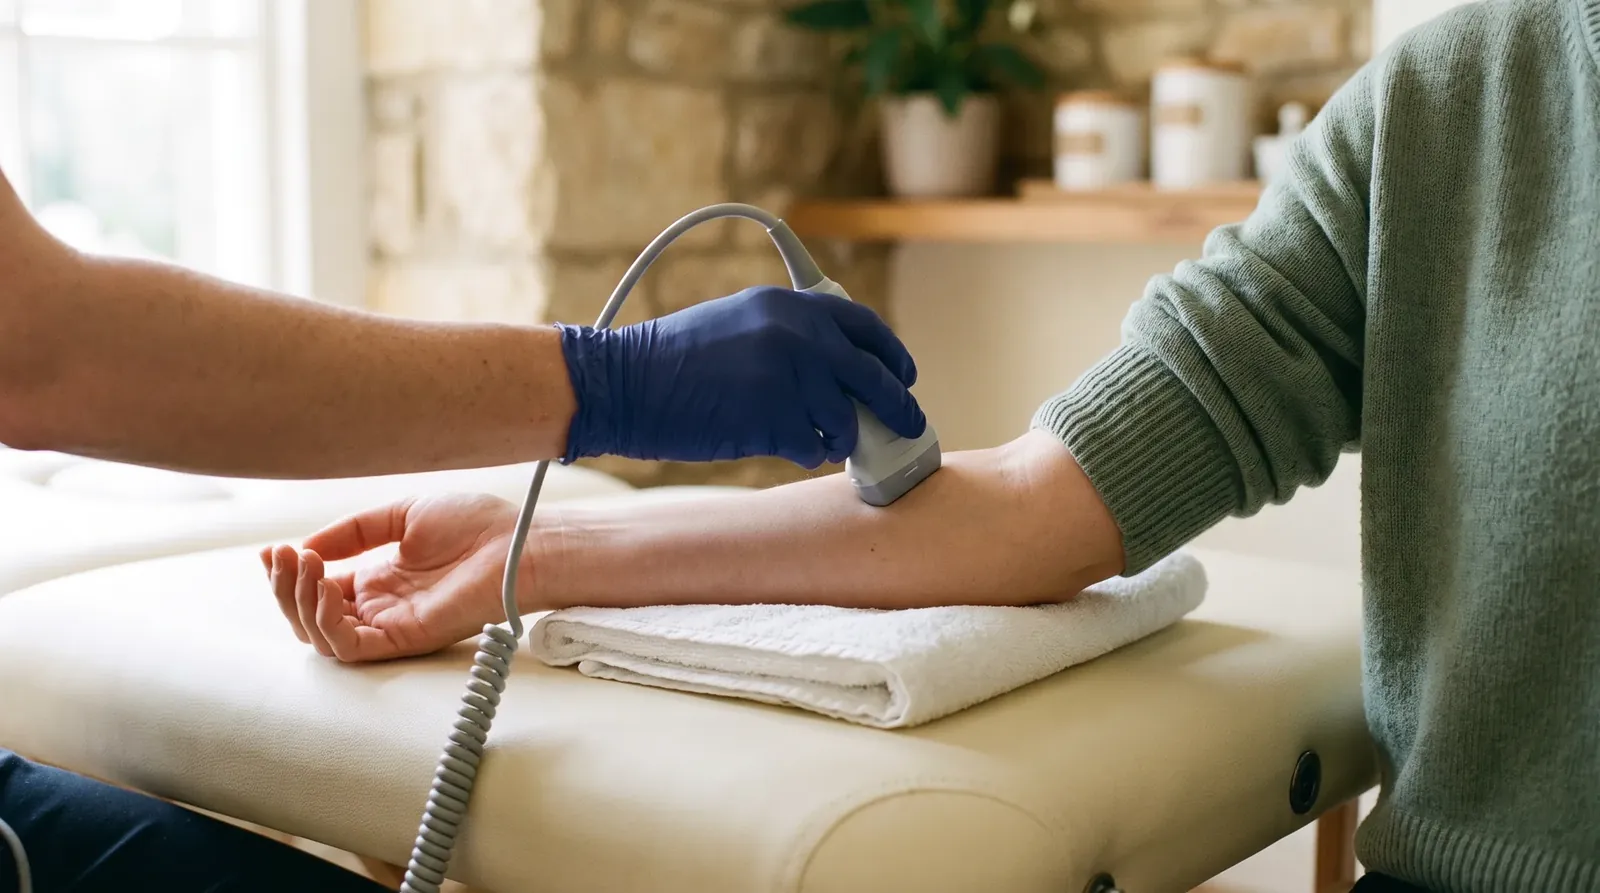
Examination, with ultrasound where it helps
The diagnosis is usually clear, and the right sequence of care tends to work.
Elbow tendon pain rarely troubles you at rest. It catches you mid-task: lifting, gripping, turning. Whether you feel it on the outer or the inner side is often the first clue.
Outer elbowLifting a cast-iron pan off the hob, palm down, and a sharp pain flares on the outer side of the elbow. It's often worse with gripping, lifting and rotating the wrist.
Often seen with Tennis elbow → Inner elbow
A firm handshake, a heavy shopping bag or a morning of repetitive forearm work, and this time the ache sits on the inner side of the elbow.
Often seen with Golfer's elbow → Outer elbow
Turning a stiff door knob, a key or a tight lid rotates the forearm under load, and the outer side of the elbow complains.
Often seen with Tennis elbow →Tennis elbow isn't limited to people who play tennis, and golfer's elbow isn't limited to golfers. Both are usually overuse-related.
Tap a point on the elbow, or choose what you're feeling. These are the patterns of elbow pain we most commonly assess. The list isn't diagnostic: your consultation works out which (if any) fits your symptoms.
Choose a point on the elbow, or a symptom above.
Left elbow, seen from behind. Hotspot positions and the ulnar nerve path are simplified illustrations.
An injection can settle the pain. What rebuilds a tendon is load, added gradually. The two often work best together, and not everyone needs the injection.

When pain is stopping you, a targeted injection can settle it: steroid for a severe, acute flare, or PRF once the problem has become chronic. For a while, the gripping and lifting that aggravate it are eased back, not stopped.
Then the tendon is loaded again, gradually: slow, controlled exercises for the forearm muscles that attach at the elbow, built up over the following weeks. This is the part that helps a tendon adapt.
The pan, the handshake, the door knob, then work and sport. Changing how the elbow is loaded, at work, in sport or both, helps keep the gains.
Move the timeline to see the idea. Simplified, not to scale.
Patterns of pain matter as much as imaging. Below are the routes we most often discuss for elbow problems. Final recommendation always follows in-person assessment.
Acute tennis or golfer's elbow with severe pain limiting work and daily use.
Useful for shorter-term relief in acute presentations to allow rehabilitation to start, but generally not repeated multiple times: the evidence for repeated steroid injections in tendinopathy is limited.
Read more about steroid injection →Chronic tennis or golfer's elbow that has not progressed with physiotherapy and brief steroid use, typically 6+ months of symptoms.
PRF is one of the better-supported options for chronic lateral and medial epicondylitis where conventional approaches have plateaued. Autologous, no synthetic additives, considered after structural assessment on ultrasound.
Read more about PRF →Olecranon bursitis with clear swelling at the tip of the elbow.
Olecranon bursitis needs careful assessment to exclude infection, gout and other systemic causes before any injection. Where it's a mechanical, non-infective presentation, aspiration and a steroid injection may be considered.
Read more about the appropriate route →Treatments are considered after clinical assessment. We do not offer or recommend injection therapy without first confirming the diagnosis and screening for contraindications.
A hot, red, rapidly swelling elbow, especially if you feel feverish or unwell, can be a sign of infection. Please seek same-day medical advice from your GP, NHS 111 or A&E rather than waiting for a routine appointment.
Most patients can continue normal activities the day after most elbow injections. The longer-term plan nearly always includes modifying how the elbow is being loaded: work, sport or both.
Timings vary from person to person. We discuss the realistic likelihood of benefit at your consultation.
Our GP-led clinic in Higher Bebington serves patients from across Merseyside: Liverpool, Birkenhead, Heswall and Chester. We assess in person before any treatment is offered, and refer onward when it's the right call.
We know it can feel difficult to book a procedure when you are not sure what will happen next. Your clinician will explain suitability, risks, recovery and aftercare before treatment goes ahead.
Choose a consultation online or speak to the clinic if you are not sure which service fits. Most appointments are available within seven days.
An in-person review with Dr Mugerwa: he will listen to your story and examine the area, which may include an ultrasound scan. You then get an honest recommendation: if treatment is suitable we explain the options, risks and likely outcomes; if it is not, we will tell you and refer you on.
The procedure itself, followed by tailored aftercare guidance and a clear contact route if anything changes during recovery.
The questions patients most often raise in clinic when they're not sure which next step is right.
There's a place for a steroid injection in acute tennis elbow, particularly when severe pain is preventing rehabilitation. However, repeated steroid injections for chronic tendinopathy don't tend to help and may slow tissue recovery. For chronic, well-established lateral epicondylitis, regenerative options such as PRF often make more sense than another steroid injection.
They're effectively the same problem at different ends of the elbow. Tennis elbow is tendinopathy of the common extensor origin on the outer side; golfer's elbow is tendinopathy of the flexor origin on the inner side. Both are usually overuse-related, both respond to similar conservative care, and both can be considered for PRF when chronic.
Any injection carries some small risk of post-injection flare, skin changes (with steroid), bruising and very rarely infection. We discuss the specific risks for your situation honestly before any treatment, and structure the recommendation so that injection isn't the default: only the right step when supported by your examination and history.
Most patients can continue normal activities the day after most elbow injections, though we usually advise resting the affected arm from heavy or repetitive loading for 48 hours. Light office or computer work is generally fine. The longer-term plan to settle the tendinopathy nearly always includes modifying how the elbow is being loaded: work, sport or both.