

The jar that won't open.
Breakfast, and a familiar burning ache at the base of the thumb as you twist the lid. Pinch grip, writing and holding a steering wheel can bring on the same pain.
Often seen with Base-of-thumb arthritis →Tingling at night? A finger that catches?

Jar lids, keys, a pen?
The hand and wrist do an extraordinary amount of work, and they tend to tell you about it.
Night-time tingling, a finger that catches on bending, thumb-side wrist pain on gripping, or that burning pain at the base of the thumb on opening a jar: these are some of the most disruptive symptoms we see, because they interfere with sleep, work and the small ordinary tasks that keep daily life moving.
At the Skin & Joint Injection Clinic in Bebington, Wirral, we assess hand and wrist problems in person, including examination and ultrasound where it helps. Where a well-placed injection is the right step, we explain the realistic likelihood of benefit and the alternatives, including surgical referral when that's the better path.
Breakfast, and a familiar burning ache at the base of the thumb as you twist the lid. Pinch grip, writing and holding a steering wheel can bring on the same pain.
Often seen with Base-of-thumb arthritis →
Pain on the thumb side of the wrist when you grip and lift: a kettle, shopping, a grandchild. Repetitive thumb use keeps it going.
Often seen with De Quervain's tenosynovitis →
In the garden, a finger clicks or locks as you open and close your grip. Sometimes there's a tender nodule you can feel in the palm.
Often seen with Trigger finger →
Numbness and pins-and-needles in the thumb, index and middle fingers, often at night or after sustained gripping. Many people shake the hand to get the feeling back.
Often seen with Carpal tunnel syndrome →Tap a point on the hand, or choose what you're feeling. These are the patterns we most commonly assess. The guide isn't diagnostic: your consultation works out which (if any) fits your symptoms.
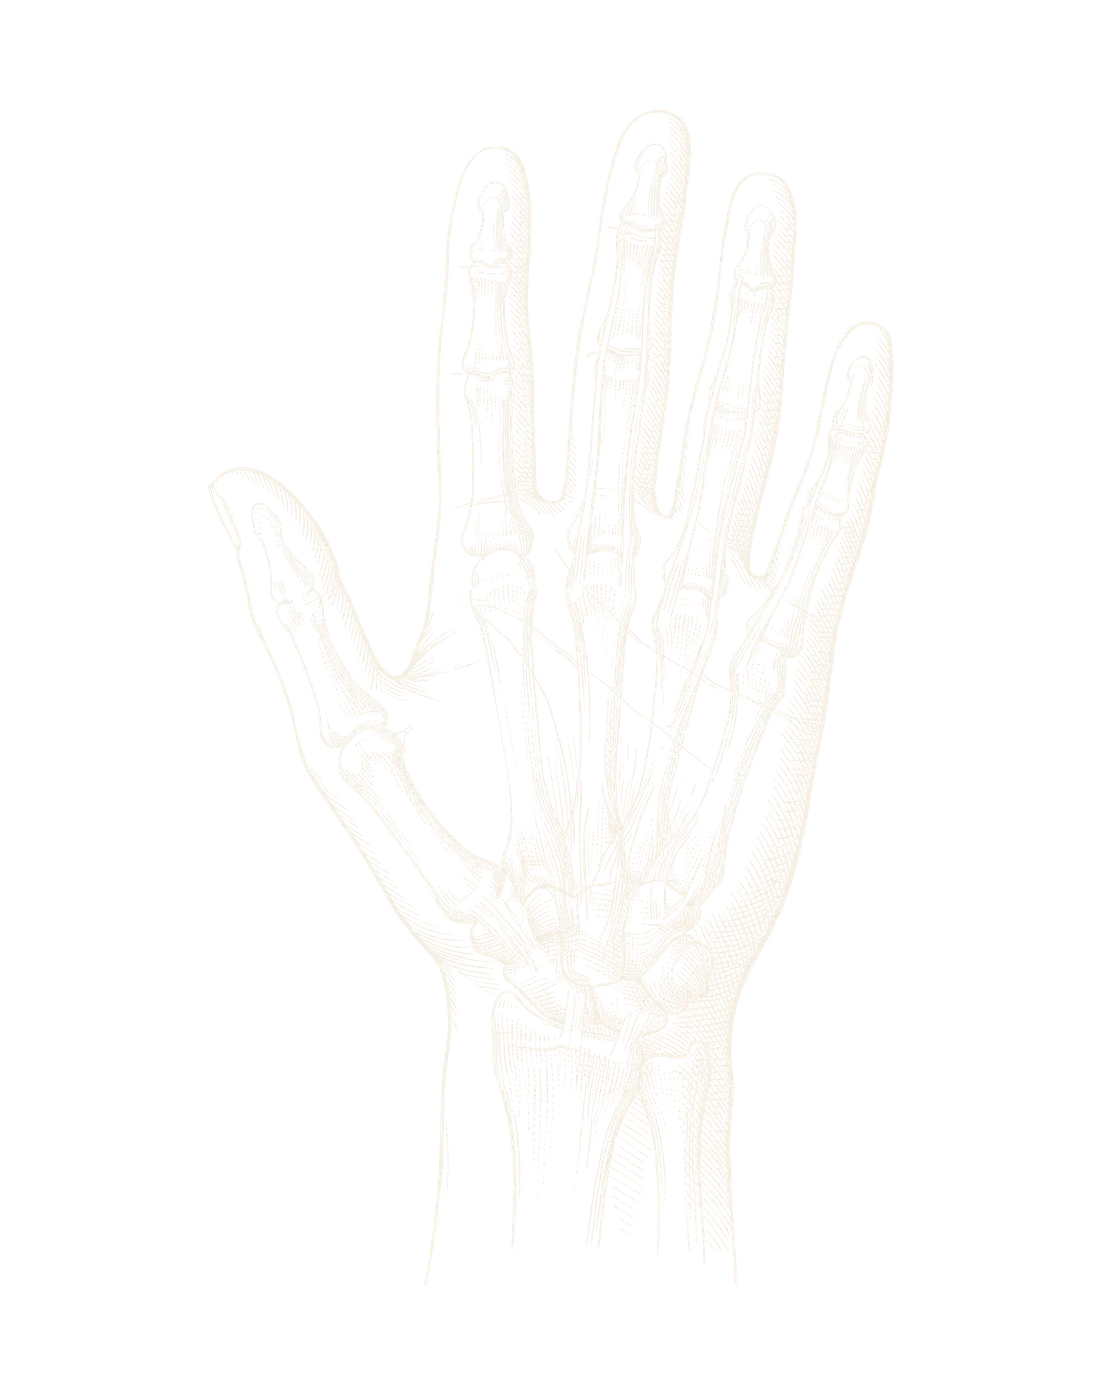
Choose a point on the hand, or a symptom above.
Nerve path shown as a simplified illustration.
An injection is rarely the whole answer for a hand. It is often the step that makes the rest of the plan possible.
Calming nerve compression, an inflamed tendon sheath or an arthritic thumb joint can ease pain and the night-time symptoms that break your sleep.
With symptoms quieter, splinting, activity changes and hand exercises become far easier to stick with, which is what keeps problems from returning.
When inflammation or nerve compression settles, many patients notice grip and dexterity improving over the weeks that follow.

At the wrist, the median nerve shares a narrow tunnel with nine tendons. Ultrasound lets us see the nerve and place the injection around it, rather than relying on surface landmarks alone.
Patterns of pain matter as much as imaging. Below are the routes we most often discuss for hand and wrist problems. Final recommendation always follows in-person assessment.
Carpal tunnel syndrome with predominantly night-time numbness and tingling, hand strength still preserved.
A targeted ultrasound-guided injection around the median nerve. Often a useful alternative to surgery in mild-to-moderate carpal tunnel syndrome, particularly when symptoms have not progressed to muscle wasting or significant weakness.
Read more about steroid injection →Trigger finger with painful catching or locking of one or more fingers.
Targeted into the A1 pulley tendon sheath. Frequently effective in early trigger finger; some patients eventually need surgical release if catching persists or recurs.
Read more about steroid injection →De Quervain's tenosynovitis with thumb-side wrist pain on gripping.
An ultrasound-guided injection into the first dorsal compartment is often a turning point for De Quervain's, particularly in new parents and patients with stubborn symptoms despite splinting and activity modification.
Read more about steroid injection →Base-of-thumb arthritis with painful pinch grip: the joint surface is the driver, not inflammation alone.
A non-steroid option for the small joints affected by osteoarthritis, including the base of the thumb. Considered where supporting lubrication is preferred over suppressing inflammation.
Read more about Ostenil Plus →Treatments are considered after clinical assessment. We do not offer or recommend injection therapy without first confirming the diagnosis and screening for contraindications.
Timings vary from person to person. We discuss the realistic likelihood of success at your consultation.
Our GP-led clinic in Higher Bebington serves patients from across Merseyside: Liverpool, Birkenhead, Heswall and Chester. We assess in person before any treatment is offered, and refer onward when it's the right call.
The questions patients most often raise in clinic when they're not sure which next step is right.
For many patients with mild-to-moderate carpal tunnel syndrome, yes: a well-targeted ultrasound-guided injection often settles night symptoms and tingling, and the benefit can last from several months to over a year in suitable cases. Where symptoms are advanced (constant numbness, muscle wasting, significant weakness), surgical release is usually the better answer, and we refer on rather than injecting repeatedly.
Many patients notice the catching or locking ease within the first one to two weeks, with full effect over three to four weeks. Some patients have a single injection and the trigger finger settles permanently; others need a second injection or, occasionally, surgical release. We discuss the realistic likelihood of success based on how long the trigger finger has been present and how severe the catching is.
Most cases of De Quervain's tenosynovitis settle with a combination of activity modification, a thumb-spica splint and, where needed, a targeted ultrasound-guided steroid injection. Surgery is reserved for resistant cases that don't respond to one or two well-placed injections.
The injection itself doesn't usually affect grip strength. The diagnosis driving the pain often does, of course: carpal tunnel, severe trigger finger and arthritic change can all reduce grip. When the injection settles inflammation or nerve compression, many patients notice grip and dexterity improving over the weeks that follow.
