

The first steps hurt the most.
Out of bed, and a sharp jab under the heel on the way to the bathroom. After a few minutes of walking it eases, then comes back after sitting down again or a long spell on your feet.
Often seen with Plantar fasciitis →Sharp heel pain on your first steps?
Assessment for plantar fasciitis, Achilles tendinopathy, ankle arthritis and Morton's neuroma.

Heel, arch or Achilles?
Foot and ankle pain has a way of dictating the day.
That sharp jab of heel pain on the way to the bathroom in the morning, the ache that creeps back at the Achilles after a walk, the burning 'stone-in-the-shoe' feeling between the toes: these are some of the most quietly limiting symptoms we see in clinic, because they affect mobility itself.
At the Skin & Joint Injection Clinic in Bebington, Wirral, we assess foot and ankle pain in person, with examination and ultrasound where it helps. Some presentations respond well to a single well-targeted injection; others benefit more from structured rehabilitation, footwear changes or referral. The recommendation always follows the assessment.
Out of bed, and a sharp jab under the heel on the way to the bathroom. After a few minutes of walking it eases, then comes back after sitting down again or a long spell on your feet.
Often seen with Plantar fasciitis →
The back of the heel and lower calf feel stiff and sore as you come downstairs. It loosens as you get going, then aches again after exercise.
Often seen with Achilles tendinopathy →
Burning pain between the toes and a sensation like walking on a stone, sometimes with numbness. The cause is a thickened nerve between the metatarsal heads.
Often seen with Morton's neuroma →
On a coastal path or uneven ground, the ankle aches as it takes your weight and doesn't bend the way it used to. It's often related to old fractures or recurrent sprains.
Often seen with Ankle osteoarthritis →These are the patterns of foot & ankle pain we most commonly assess. Tap a point on the foot, or choose what you're feeling. The list isn't diagnostic: your consultation works out which (if any) fits your symptoms.
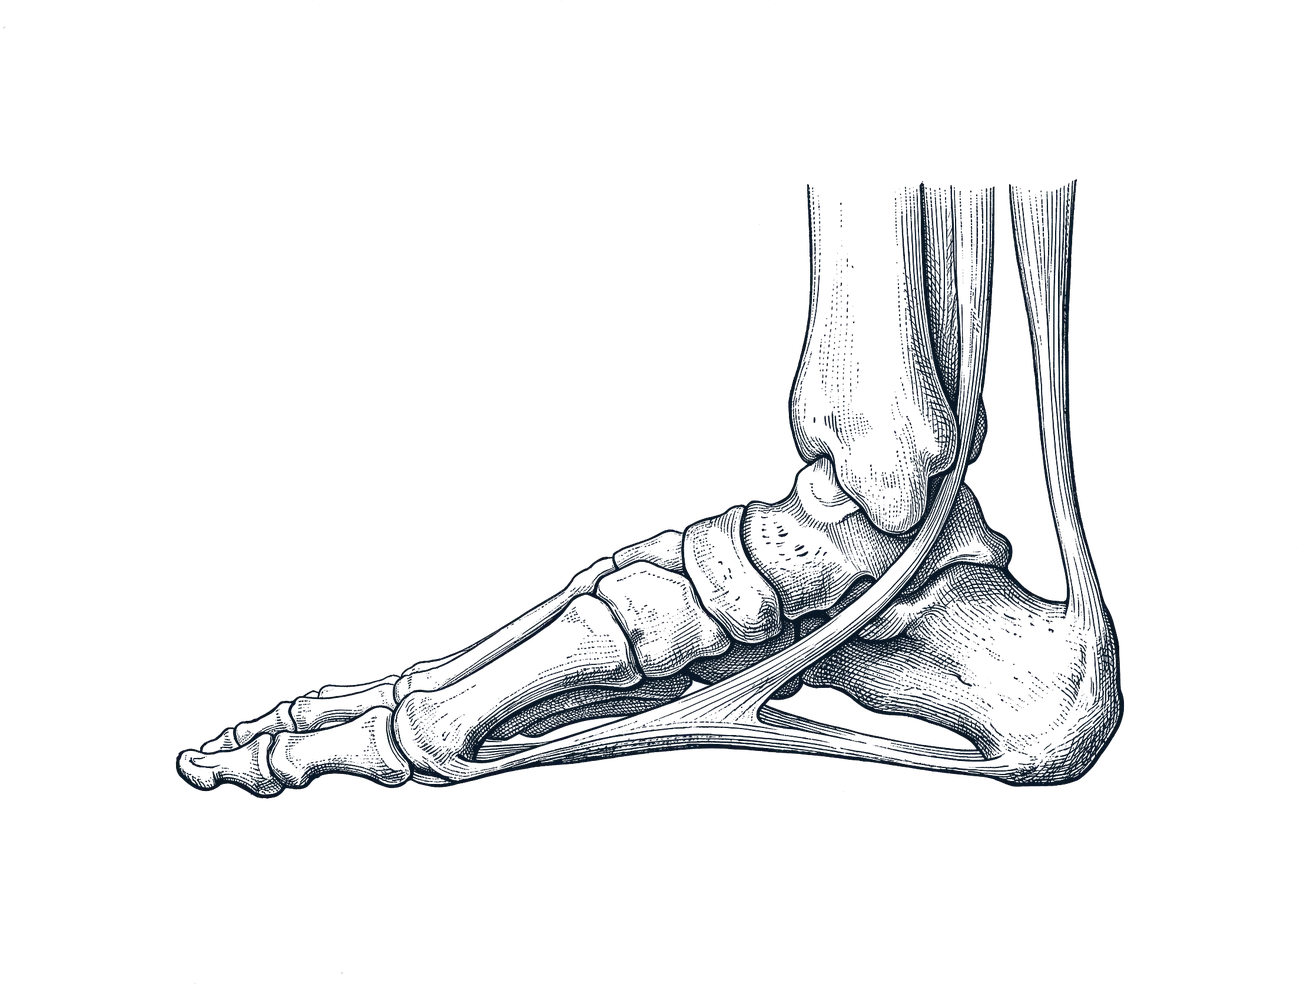
Choose a point on the foot, or a symptom above.
Hotspot positions and the tendon and nerve paths are simplified illustrations.
Treatment usually combines stretching, footwear changes and load management (and, in stubborn cases, a targeted injection) rather than relying on any single intervention.
A targeted injection can calm a stubborn plantar fascia or the irritated nerve of a Morton's neuroma, with heavy or prolonged loading avoided for 48 hours. For the Achilles, PRF rather than steroid.
Calf and plantar fascia stretching, supportive footwear, and loading built back gradually. For the Achilles, eccentric loading is the foundation.
The first steps of the morning, the stairs, the walk into town, the coastal path. For running and court sport, a longer rest period and a gradual return.

Calf and plantar fascia stretching
Plans are tailored to your diagnosis. Responses vary, and not everyone needs an injection.
Patterns of pain matter as much as imaging. Below are the routes we most often discuss for foot & ankle problems. Final recommendation always follows in-person assessment.
Chronic plantar fasciitis with sharp heel pain on first steps despite structural rehab and stretching.
An ultrasound-guided injection into the plantar fascia. Best used selectively rather than repeatedly, paired with calf and fascia stretching and supportive footwear.
Read more about steroid injection →Plantar fasciitis where steroid hasn't helped or repeated steroid use is not appropriate.
A regenerative option for chronic plantar fasciitis. Autologous, no synthetic additives, considered after careful structural assessment on ultrasound.
Read more about PRF →Chronic Achilles tendinopathy that has not progressed despite eccentric loading and rehabilitation.
Achilles tendinopathy is generally not managed with steroid injection: the risk of tendon rupture is real. PRF provides an autologous, biology-led alternative for chronic mid-portion or insertional Achilles pain.
Read more about PRF →Ankle osteoarthritis with restricted movement and pain on weight-bearing.
Considered for arthritic ankle pain where supporting joint lubrication is the goal. Ostenil Plus is more versatile across joints; Durolane is considered in selected cases where a single longer-acting shot is preferred.
Read more about hyaluronic acid →Morton's neuroma with burning forefoot pain and a 'stone-in-the-shoe' sensation between the toes.
A targeted ultrasound-guided injection around the affected interdigital nerve. Often helpful in early-to-moderate Morton's neuroma alongside footwear modification.
Read more about steroid injection →Treatments are considered after clinical assessment. We do not offer or recommend injection therapy without first confirming the diagnosis and screening for contraindications.
We know it can feel difficult to book a procedure when you are not sure what will happen next. Your clinician will explain suitability, risks, recovery and aftercare before treatment goes ahead.
Choose a consultation online or speak to the clinic if you are not sure which service fits. Most appointments are available within seven days.
An in-person review with Dr Mugerwa: he will listen to your story and examine the area, which may include an ultrasound scan. You then get an honest recommendation: if treatment is suitable we explain the options, risks and likely outcomes; if it is not, we will tell you and refer you on.
The procedure itself, followed by tailored aftercare guidance and a clear contact route if anything changes during recovery.
Our GP-led clinic in Higher Bebington serves patients from across Merseyside: Liverpool, Birkenhead, Heswall and Chester. We assess in person before any treatment is offered, and refer onward when it's the right call.
The questions patients most often raise in clinic when they're not sure which next step is right.
First-step heel pain is the most characteristic feature of plantar fasciitis. While you've been resting overnight, the inflamed plantar fascia tightens; the first few steps stretch it sharply, which is what causes the sharp pain. The pain usually eases after a few minutes of walking, then returns later in the day with prolonged standing or after sitting down again.
Steroid injection directly into the Achilles tendon is generally avoided: there's a recognised risk of tendon rupture. Where Achilles tendinopathy hasn't responded to eccentric loading, footwear changes and time, regenerative options such as PRF are usually a safer next step. We assess the structure on ultrasound before recommending any injection-based treatment around the Achilles.
Weight and prolonged standing are contributors, but plantar fasciitis affects active runners and slim people too. Calf and fascia tightness, sudden changes in activity, unsupportive footwear and foot biomechanics all play a part. Treatment usually combines stretching, footwear changes, load management (and, in stubborn cases, a targeted injection) rather than relying on any single intervention.
Most patients walk out of clinic and resume ordinary daily activities the same day, with advice to avoid heavy or prolonged loading for 48 hours. For high-impact activity (running, court sport), we usually recommend a longer rest period and a gradual return. Written aftercare guidance is given before you leave.